
Understanding Other Aggressive B-Cell Lymphomas
Burkitt, primary mediastinal B-cell, transformed
Overview
B-Cell lymphomas are a type of blood cancer that affects B-cells (a type of white blood cell that helps the body fight infection) and mainly appears in the lymph nodes (small bean-shaped structures that help the body fight disease). Primary mediastinal large B-cell lymphoma, Burkitt lymphoma, transformed lymphomas, and post-transplant lymphoproliferative disorders are B-cell lymphomas which account for 85% of all non-Hodgkin lymphoma (NHL). B-cell lymphomas can be indolent (slow growth), or aggressive (it grows faster and can quickly spread to other parts of the body).
Burkitt lymphoma (BL) is a rare but very aggressive form of mature (fully developed) B-cell lymphoma. The disease typically involves younger patients and is the most common type of pediatric (in children from birth to young adulthood) NHL. It may also be seen in elderly patients. It may affect different parts of the body, such as the bowel, kidneys, jaw, bones, or ovaries. In some cases, it may spread to the central nervous system (CNS, the brain and spinal cord). At diagnosis, a sample of cerebrospinal fluid (the fluid that flows in and around the CNS) may be taken to determine if the disease has spread to the CNS.
Primary mediastinal B-cell lymphoma (PMBCL) is a rare subtype of aggressive B-cell lymphoma that is diagnosed mostly in adolescents and young adults and constitutes 2-3% of all cases of NHL. PMBCL is a form of diffuse large B-cell lymphoma (DLBCL) that appears in the thymus gland (small organ located in the upper chest that makes white blood cells) and is usually limited to the mediastinum (a compartment in the central part of the chest that includes the heart, thymus, esophagus, and trachea). Most patients are 30 to 40 years of age at diagnosis, and the disease is more common in women.

Transformed lymphoma occurs when genetic mutations (permanent changes) in the DNA (deoxyribonucleic acid, the molecule that carries genetic information within the cell) in some indolent lymphoma cells cause them to grow faster and behave more aggressively (see Table 1). Not all of the indolent lymphoma cells undergo transformation at once. When examined under the microscope, biopsies (samples of lymph nodes) from patients with transformed lymphomas will usually have a combination of indolent and aggressive (“transformed”) lymphoma cells. If the number of fast-growing cells increases, the lymphoma can begin to behave more like an aggressive type. Compared to indolent lymphomas, this transformed lymphoma usually requires more intensive types of treatment.

Table 1. Examples of Transformation
| Indolent Lymphoma | Transformed Lymphoma |
|---|---|
| CLL/SLL | DLBCL (Richter syndrome) HL (uncommon) |
| FL (grades 1-2) Grade 1-3A FL are low-grade (slow growing) lymphomas. Grade 3B is treated as an aggressive (fast-growing) lymphoma. | DLBCL High-grade lymphoma with mutations in the MYC and BCL2 and/or BCL6 genes (a piece of DNA that contains information needed to produce the MYC and BCL2 proteins, respectively). This type is also known as double hit lymphoma. |
| WM | DLBCL |
| MZL | DLBCL |
| Nodular lymphocyte-predominant HL (also called nodular lymphocyte predominant B-cell lymphoma) | DLBCL |
Post-transplant Lymphoproliferative Disorder (PTLD) is a life-threatening complication in 2-20% of patients who underwent organ transplantation or a donor stem cell transplant (SCT, the patient is treated with high-dose chemotherapy (drugs that stop the growth of or kill cancer cells)) or radiation to remove their blood-forming cells or stem cells, and then receives healthy stem cells to restore the immune system and the bone marrow’s ability to make new blood cells). It is associated with the Epstein-Barr virus (EBV) that can be acquired from the transplant donor or the environment.
Symptoms, Staging, and Diagnostic Procedure
Burkitt Lymphoma
The cancer cells in BL have a permanent change (genetic mutation) in a part of their DNA called a translocation (Figure 1) of the MYC gene. This translocation is only found in the lymphoma cells (not on healthy cells) and is used to diagnose the disease.
In adults, BL is sometimes difficult to distinguish (tell apart) from different types of NHL called high grade B-cell lymphoma (HGBCL) or DLBCL—a more common form of aggressive B-cell NHL. It is very important for doctors to distinguish BL from HGBCL and DLBCL, because each disease is treated differently.
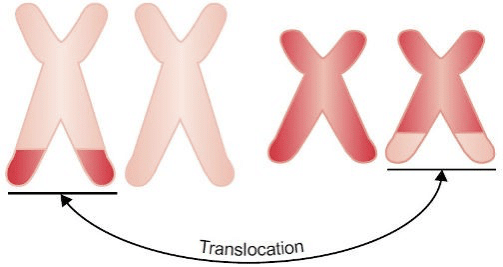
Figure1.Translocation of the MYC gene, where a chromosome breaks and part of it reattaches to another chromosome.
There are three main types of BL:
- Endemic BL typically affects boys between the ages of 4 and 7 years in specific parts of the world (Equatorial Africa, Papua New Guinea, and regions of South America), where it is the most common childhood cancer. Endemic BL is linked to an infection with EBV and is rare outside these specific areas. However, the majority of people who have EBV infection will not develop endemic BL.
- Sporadic BL occurs in children and adults worldwide. It makes up about 1-2% of NHLs in adults and is one of the most common types of childhood lymphoma in the US.
- Immunodeficiency-associated BL is most common in people with human immunodeficiency virus/acquired immunodeficiency syndrome (HIV/ AIDS, a condition where the immune system is weakened and unable to fight common infections). This type of BL can also occur in patients who have inherited immune deficiencies or who take immunosuppressive medications to prevent rejection after organ transplant, or other reasons. However, most people with these conditions will not develop immunodeficiency-associated BL.

Primary mediastinal B-cell lymphoma
Symptoms of PMBCL include cough, chest pain, fever, weight loss, night sweats, shortness of breath, and superior vena cava syndrome, which is a swelling of the face and arms caused by compression of the major vein that delivers blood to the heart. Patients with PMBCL usually have a better prognosis than those with other subtypes of DLBCL, and most patients can be cured.
Transformed lymphoma
For transformed lymphomas, multiple risk factors associated with transformation have been identified, even though the presence of a risk factor does not mean that the lymphoma will transform. The overall risk of developing a transformed lymphoma is low among patients with an indolent disease, with an average risk of 2 to 3% per year that may stabilize (no longer increase) beyond 6 to 12 years after diagnosis. This means that the majority of these patients will never develop a transformed lymphoma. Patients who develop TL may have symptoms such as cough, chest pain, weight loss, and night sweats.
Post-transplant Lymphoproliferative Disorder
PTLD symptoms can be highly variable and present as localized or spread disease. The most common symptoms are fever, night sweats, and weight loss. A detailed medical history and physical examination combined with other tests such as complete blood cell count, EBV status, urine analysis, lactate dehydrogenase levels, imaging studies, and cerebral spinal fluid analysis, are essential for a diagnosis.

There are 4 main PTLD subtypes:
- Monomorphic PTLD is the most common type of PTLD (around 70% of PTLD) and includes DLBCL, BL, plasma cell myeloma, and plasmacytoma-like PTLD.
- Polymorphic PTLD consists of about 15-20% of all PTLD and includes polymorphic cells (more than one type of cell).
- Early lesions are about 5% of all PTLD and include plasmacytic hyperplasia (plasma cell multiplication usually due to the need to fight infection), infectious mononucleosis (contagious disease caused by viruses, mainly EBV), and florid follicular hyperplasia (increase in organ tissue due to uncontrolled cell multiplication).
- Classical Hodgkin-like PTLD is the rarest form (less than 5%) of PTLD and is often diagnosed after transplantation. This type is similar to classical HL with Reed-sternberg cells (very large, abnormal white blood cells).
Treatment Options
First Treatment after Diagnosis
The choice of initial therapy for aggressive B-cell lymphomas depends on different factors, such as the patient’s age, the presence of other medical conditions (sometimes referred to as co-morbidities), disease stage (how much the cancer has grown and if it has spread to other parts of the body), and risk level (low-risk to high-risk). Doctors determine the risk level based on the results of tests and scans, and on how the disease is affecting the patient’s daily life.
Burkitt Lymphoma
Since BL is very aggressive, diagnosis is often a medical emergency, requiring urgent hospitalization and treatment. BL is usually very responsive to intensive (given at high doses or over several months) combination chemotherapy regimens and cure rates (the percentage of patients who get cured from the cancer) are high. Therefore, standard of care (the proper treatment that is widely used by healthcare professionals and accepted by medical experts) treatment typically involves short courses of intensive chemotherapy regimens in combination with the monoclonal antibody (proteins made in the laboratory that bind to markers at the surface of cancer cells and helps the body fight cancer) rituximab (Rituxan). Less intensive regimens might be used for patients with low-risk BL or who are not fit for intensive chemotherapy. Specific chemotherapy treatment options for adults include the regimens listed in Table 2.

Table 2. Common Intensive Chemotherapy Regimens Used to Treat Patients with BL.
| Chemotherapy regimens | Agents (Drugs) |
|---|---|
| Dose-adjusted EPOCH-R (DA EPOCH-R) | Etoposide (Etopophos, Toposar, VePesid), prednisone, vincristine (Oncovin, Vincasar), cyclophosphamide, and doxorubicin plus rituximab (Rituxan; a monoclonal antibody frequently combined with chemotherapy). Intrathecal (injected into the cerebrospinal fluid) methotrexate for patients who are at low risk and without CNS involvement, or high-risk patients who are not able to tolerate more aggressive treatments. |
| HyperCVAD | Cyclophosphamide, vincristine, doxorubicin, and dexamethasone alternating with high-dose methotrexate and cytarabine (Cytosar). If rituximab (Rituxan) is added, the regimen is called R+HyperCVAD. Intrathecal therapy may be given for a longer duration than the other treatments listed herein. |
| CODOX-M/IVAC | Cyclophosphamide, doxorubicin, and vincristine with intrathecal methotrexate and cytarabine, followed by high-dose systemic (throughout the body) methotrexate with or without rituximab, for three cycles. This regimen is combined with IVAC (ifosfamide, intrathecal methotrexate, etoposide, and high-dose cytarabine) for the treatment of BL in adult patients and children. |
| CALGB | Cyclophosphamide, prednisone, ifosfamide, methotrexate, vincristine, cytarabine, etoposide, doxorubicin, and dexamethasone. If rituximab (Rituxan) is added, the regimen is called R+CALGB. Outcomes improved for R+CALGB. |
| LMB | Cyclophosphamide, doxorubicin, vincristine, and prednisone. If rituximab (Rituxan) is added, the regimen is called R+LMB. Intermediate or high-risk groups may additionally receive regimens including cytarabine, methotrexate, and etoposide. |
Other types of treatment for BL can include chemoimmunotherapy which is a combination of chemotherapy with immunotherapy (drugs that use the body’s immune system to fight cancer), and monoclonal antibodies.
Primary mediastinal B-cell lymphoma
PMBCL treatment typically begins shortly after diagnosis. The aim is to achieve durable remission (disappearance of signs of cancer for a long period) or cure. A combination of chemotherapy and a monoclonal antibody targeting CD20 (a protein found at the surface of lymphoma cells) remains the backbone of most treatments. The most commonly used anti-CD20 monoclonal antibody is rituximab (Rituxan), and it is given intravenously (injected into a vein). Rituxan and hyaluronidase human (Rituxan Hycela), a form of rituximab that is injected subcutaneously (under the skin), may be an option for some patients.
The regimen EPOCH-R (etoposide, prednisone, vincristine, cyclophosphamide, doxorubicin, and rituximab) is the standard of care for PMBCL. The RCHOP (rituximab, cyclophosphamide, doxorubicin, vincristine, and prednisone) combination regimen is typically followed by radiation therapy. This regimen is usually given in 21-day cycles (a period of treatment followed by a period of rest that is repeated on a regular schedule). For many patients with PMBCL, the initial treatment can lead to disease remission or a cure.

For more information about SCT, please view the Understanding Cellular Therapy Guide on the Lymphoma Research Foundation’s website (visit lymphoma.org/publications).
Transformed lymphoma
Treatment for transformed lymphoma usually includes aggressive chemotherapy regimens, which vary depending on the clinical condition (signs and symptoms of disease and overall health) of the patient.
The type of treatments for transformed lymphoma may include any of the following (Table 3):
- Chemotherapy
- Immunotherapy with monoclonal antibodies
- SCT
- Targeted therapies (drugs that target molecules that cancer cells use to grow and spread).
- Chimeric antigen receptor (CAR)
- T-cell therapies (a special type of immunotherapy that uses the patient’s immune cells to fight cancer). Patients seeking more information about stem cell transplantation and/or CAR T-cell therapy should view the Understanding Cellular Therapy guide on the Foundation’s website (lymphoma.org/publications).
- Chemoimmunotherapy:
- A common approach is the combination of chemotherapy with a monoclonal antibody that targets CD20 (a protein at the surface of cancer cells), such as rituximab (Rituxan). Subcutaneous rituximab (Rituxan Hycela) or rituximab biosimilars (like rituximab-abbs and rituximab-pvvr) are often used.
- Biosimilars are drugs that are modeled after a biologic therapy that already exists. To learn more, please see the Understanding Lymphoma Biosimilar Therapies Factsheet on the Foundation’s website at lymphoma.org/publications

Table 3. Available Treatment Options for Transformed Lymphoma
| Agents (Drugs) | Class of drug (type of treatment) and approved indication |
|---|---|
| Tafasitamab-cxix (Monjuvi) | Immunotherapy; anti-CD19 monoclonal antibody. Approved for patients with DLBCL arising from low-grade lymphoma. Tafasitamab can be combined with lenalidomide for an improved effect on the body. |
| Loncastuximab tesirine (Zynlonta) | Immunotherapy; anti-CD19 ADC. DLBCL arising from low-grade lymphoma, and high-grade B-cell lymphoma. |
| Epcoritamab (Epkinly) Glofitamab (Columvi) | Immunotherapy; Bispecific anti-CD20 antibodies. DLBCL arising from indolent lymphoma. |
| Axicabtagene ciloleucel (Yescarta) Tisagenlecleucel (Kymriah) Lisocabtagene maraleucel (Breyanzi) | CAR T-cell therapy Approved for patients with DLBCL arising from FL. |
| Selinexor (Xpovio) | Targeted therapy; XPO1 inhibitor. Approved for patients with DLBCL arising from FL. |
Post-transplant Lymphoproliferative Disorder
The most common treatment options for PTLD include:
- Reduction of immunosuppression (when the immune system ability to fight disease is reduced which can be achieved through medication used to prevent transplant rejection): reduction in at least 50% of the immunosuppression or stopping treatment.
- Surgical removal of the localized lesion
- Radiation therapy: used in patients with localized disease and those with CNS involvement either alone or in combination.
- Chemoimmunotherapy: indicated in patients who had a limited response to reduced immunosuppression and rituximab. It is usually administered in combination with rituximab for patients with CD20+ PTLD.
- Chemotherapy: R-CHOP (rituximab plus cyclophosphamide, doxorubicin, vincristine, and prednisone) is commonly used in chemotherapy regimen for most patients with PTLD.
- Immunotherapy: Rituximab is commonly used in patients with PTLD.
Relapsed or Refractory Aggressive B-cell Lymphomas
Some patients with aggressive B-cell lymphomas respond to initial treatment and go into remission. In other cases, the disease may relapse (disease returns after treatment) or become refractory (does not respond to treatment). For these patients, different therapies may result in improved treatment outcomes.
Burkitt lymphoma
Patients with BL that has spread to the CNS, also referred to as CNS involvement, are at a higher risk of relapse (disease returns after treatment). Patients with BL without CNS involvement require prophylaxis (preventive treatment) to make sure that the disease will not affect the CNS later on. How often a person needs treatment, which are administered (given) intrathecally (injected into the spinal fluid), depends on whether or not there is CNS involvement at diagnosis.
Immunodeficiency-associated BL should be treated with similar regimens as for HIV-negative patients with BL. Antiretroviral therapy (drugs used to treat HIV infection) can be safely administered with chemotherapy. Different combination chemotherapy regimens are used to treat BL in children and adolescents, and younger patients tend to have both excellent responses to chemotherapy and high cure rates. This means that the cancer disappears after treatment and does not come back. These patients are now treated with smaller amounts of chemotherapy, which can still cure the disease but have fewer side effects.
Patients with BL that are being treated may experience tumor lysis syndrome. This means that a large number of cancer cells die in a short amount of time after treatment and flood the bloodstream with toxins, which may damage the kidneys, heart and liver.
Symptoms may include:
- Joint discomfort.
- Nausea and vomiting.
- Shortness of breath.
- Irregular heartbeat.
- Clouding of the urine.
- Lethargy (feeling drowsy and without energy).
This condition is potentially severe and can occur spontaneously or after chemotherapy. Tumor lysis syndrome can cause organ damage, seizures, loss of muscle control, and in some cases, death. However, this condition can be managed with increased fluids and supportive medications like allopurinol (Aloprim, Lopurin, and Zyloprim) or rasburicase (Elitek). It is very important that patients talk to their doctor if they experience any of the symptoms listed above.
Primary mediastinal B-cell lymphoma
Early evaluation with a team of specialists is recommended for patients with relapsed/ refractory PMBCL. Treatment options will depend on a number of factors, including when the relapse happened and whether the patient is eligible for SCT or CAR T-cell therapy.
In case of an early relapse (occurs during treatment or shortly after), CD19 CAR T-cell therapy with axicabtagene ciloleucel (Yescarta) or lisocabtagene maraleucel (Breyanzi) is recommended.
If CAR T-cell therapies are not a viable treatment option, other treatment options are available (including the therapeutic options in Table 4):
- Chemoimmunotherapy
- Involved-site radiation therapy (radiation therapy is applied to treat a specific area where the cancer is located at).
- Targeted therapy
Patients should talk to their doctors about having a consultation with a physician at an authorized CAR T center early after a relapse or if the lymphoma does not respond to the initial treatment. For more information on the CAR T-cell therapy process, please view the Understanding Cellular Therapy guide at lymphoma.org/publications.
For patients who have a late relapse (disease returns after 12 months) and are eligible for transplant, an autologous SCT is the recommended therapy. Patients that are not eligible for a transplant, are commonly treated with CAR T-cell therapy such as lisocabtagene maraleucel (Breyanzi). Patients who are not eligible for a transplant and who do not respond to CAR T-cell therapy, have several other second- and third-line treatment options available (Table 4):
- Chemotherapy
- Immunotherapy, including:
- Monoclonal antibodies such as tafasitamab-cxix (Monjuvi)
- Antibody-drug conjugates such as polatuzumab vedotin (Polivy) and brentuximab vedotin (Adcetris). The monoclonal antibody in the ADC recognizes and binds to a protein on the cancer cell surface. Once the ADC is inside the cell, the chemotherapy drug separates from the ADC and kills the cancer cell by targeting cell multiplication.
- Immunomodulatory agents, such as lenalidomide (Revlimid).
- Bispecific antibodies such as glofitamab (Columvi) and epcoritamab (Epkinly)
- Targeted therapies such as ibrutinib (Imbruvica) and selinexor (Xpovio).

Table 4. Second- and Third-Line Treatments for Relapsed or Refractory PMBCL
| Patients Who Are Candidates for a Stem Cell Transplant | |
|---|---|
| Chemotherapy is the preferred second-line treatment | DHAP +/- rituximab (Rituxan) DHAX +/- rituximab (Rituxan) GDP +/- rituximab (Rituxan) ICE +/- rituximab (Rituxan) ESHAP +/- rituximab (Rituxan) GemOx +/- rituximab (Rituxan) MINE +/- rituximab (Rituxan) |
| Patients Who Are NOT Candidates for a Stem Cell Transplant | |
|---|---|
| Chemotherapy | GemOx +/- rituximab (Rituxan) CEOP +/- rituximab (Rituxan) GDP +/- rituximab (Rituxan) or (gemcitabine, dexamethasone, carboplatin) +/- rituximab |
| Other second-line regimens | Polatuzumab vedotin (Polivy) +/- rituximab (Rituxan) and +/-bendamustine (Treanda) Tafasitamab-cxix (Monjuvi) and lenalidomine (Revlimid) Axicabtagene ciloleucel (Yescarta) Lisocabtagene maraleucel (Breyanzi) |
| After ≥ 2 lines of systemic therapy | Rituximab (Rituxan) Axicabtagene ciloleucel (Yescarta) Tisagenlecleucel (Kymriah) Lisocabtagene maraleucel (Breyanzi) Selinexor (Xpovio) Glofitamab (Columvi) Epcoritamab (Epkinly) Loncastuximab tesirine (Zynlonta) |
| Other therapies for PMBCL | Brentuximab vedotin (Adcetris) Ibrutinib (Imbruvica) Lenalidomide (Revlimid) +/- rituximab (Rituxan) Pembrolizumab (Keytruda) |
Post-transplant Lymphoproliferative Disorder
Therapy for relapsed and/or refractory PTLD include chemoimmunotherapy that can be combined with rituximab (Rituxan) and immunotherapy with EBV-specific T-lymphocytes.
Transformed lymphoma
Therapeutic options for relapsed/refractory TL may include:
- CAR T-cell therapy:
- Axicabtagene ciloleucel (Yescarta)
- Lisocabtagene maraleucal (Breyanzi)
- Autologous or allogeneic SCT
- Targeted therapy such as ibrutinib
- Chemoimmunotherapy
- Involved-site radiation therapy
Treatments Under Investigation
Many new treatments (also called investigational drugs) and combinations are currently being tested in clinical trials for patients with aggressive B-cell lymphoma. This includes patients who are newly diagnosed and those with relapsed (disease comes back after treatment) or refractory (disease does not respond to treatment) lymphoma. Participation in a clinical trial is highly encouraged when available. Results from these clinical trials may improve or change the current standard of care. Table 5 (below) lists some of these investigational drugs that can be accessed through a clinical trial. For more information on clinical trials, view the Understanding Clinical Trials fact sheet on the Foundation’s website (lymphoma.org/publications).
Table 5. Treatments Under Investigation for Treatment of Aggressive B-cell Lymphoma in Phase 2 or 3 Clinical Trials.
| Agent(s) (Drugs) | Class (Type of treatment) | Approved Indication |
|---|---|---|
| Nivolumab (Opdivo) | Immune checkpoint inhibitor; anti-PD-1 | Untreated BL, R/R BL, untreated PMBL |
| Pembrolizumab (Keytruda) | Immune checkpoint inhibitor; anti-PD-1 | Untreated BL, untreated TL, R/R PMBL |
| Ofatumumab (Arzerra) | Monoclonal antibody; anti-CD20 | Untreated BL |
| Venetoclax (Venclexta) | Targeted therapy. Bcl-2 inhibitor | Untreated BL, R/R BL, untreated TL |
| Ibrutinib (Imbruvica) | Targeted therapy; BTK inhibitor | Untreated BL |
| Obinutuzumab (Gazyva) | Monoclonal antibody; anti-CD20 | Untreated BL, untreated TL |
| Lenalidomide (Revlimid) | Immunomodulator drug | Untreated BL |
| Acalabrutinib (Calquence) | Targeted therapy; BTK inhibitor | Untreated BL, untreated TL |
| Inotuzumab ozogamicin (Besponsa) | Antibody-drug conjugate; anti-CD22 | Untreated BL |
| Polatuzumab vedotin (Polivy) | Antibody-drug conjugate; anti-CD79b | Untreated BL, untreated PTLD |
| Bortezomib (Velcade) | Targeted therapy; proteosome inhibitor | Untreated BL |
| Blinatumomab (Blincyto) | Bispecific antibody; anti-CD3 and CD19 | Untreated BL |
| Glofitamab | Bispecific antibody; anti-CD20 | R/R TL |
| Brentuximab vedotin | Antibody-drug conjugate; anti-CD30 | Untreated PMBL |
| WZTL-002 | CAR-T cell therapy; anti-CD19 | Untreated PMBL, untreated TL |
| Tafasitamab | Monoclonal antibody; anti-CD19 | Untreated PTLD |
| Loncastuximab tesirine | Antibody-drug conjugate; anti-CD19 | R/R PTLD |
| CPI-613 (Devimistat) | Targeted therapy; TCA inhibitor | R/R BL |
Post-transplant Lymphoproliferative Disorders; R/R, relapsed and/or refractory; TCA, mitochondrial tricarboxylic acid; TL, Transformed Lymphoma.
How to Be a Self-Advocate
Being a self-advocate and an active participant in healthcare decisions can be a positive experience. It may help patients regain a sense of control that they may have lost following the lymphoma diagnosis by making sure patients receive the best care. Patients and care partners should remember they are partners in their treatment plan.
- Do not be afraid to ask your doctors or nurses questions about your care. An educated patient asking questions is not ‘being a challenge to your physician’ (or ‘being a difficult patient’).
- Learn more about lymphoma by asking your doctor for information and visiting reliable websites, such as the Foundation’s at www.lymphoma.org.
- Take advantage of counseling, support groups, nutritional counseling, fitness classes, expressive arts, and other services offered at your doctor’s office, cancer center, or hospital.
- Consider joining the Foundation’s Lymphoma Support Network, a nationwide peer support program that matches patients and care partners with people who have had similar experiences. For information about the program, call (800) 500-9976 or email [email protected].
- Finally, it is important that patients not be afraid to talk with the healthcare team about nonmedical issues such as transportation, finances, insurance, working through treatment or taking time off, and childcare. There are nurses, social workers, and physician’s assistants that are able to provide the support and resources to help.

Clinical Trials
Clinical trials are crucial in identifying effective drugs and optimal treatment doses for patients with lymphoma. They are not a “last resort” for patients. Every drug available today had to be tested in clinical trials before it was approved for general use, and all new and emerging treatments. There are four main types or phases of clinical trials. The phase is based on the study’s objective and the number of participants.
Phase I
- To identify a safe dose of a new drug
- To decide on a dosing schedule for the drug
- To see what side effects are related to the therapy
Phase II
- To see if a new treatment is effective against a certain type of cancer at the dose determined in Phase I
- To confirm and learn more about the side effects identified in Phase I
Phase III
- To compare the new treatment or new use of an existing treatment with the current standard treatments
- To obtain detailed information about how well the treatment works and the types and severity of side effects it causes
Phase IV
- To look at long-term safety and effectiveness that take place after a new treatment has been approved by the FDA and is available to the public.


Patients interested in participating in a clinical trial should view the Understanding Clinical Trials fact sheet on the Foundation’s website (visit lymphoma.org/publications), and the Clinical Trials Search Request Form, talk to their physician, or contact the Foundation’s Lymphoma Resource Center for an individualized clinical trial search by calling (800) 500-9976 or emailing [email protected].
Follow-Up
Survivorship
As a cancer survivor, it is important that you practice self-care regularly to reset your physical and emotional well-being. Adopting routines of self-care will help you recharge your batteries and stay healthy. Talk with your healthcare team about developing a wellness plan to help you stay physically and emotionally healthy and improve your mood. Consider the following suggestions:
- Watch your health. Stay up-to-date with your own medical appointments and take any medications as prescribed.
- Exercise. Stay active with short periods of daily exercise (30 minutes of power walking, jogging or biking). If not possible, take the stairs instead of the elevator or park farther away than usual.
- Eat well. Include fruits and vegetables in your meals and maintain a balanced diet.
- Cut down on risk factors. Quit smoking and reduce alcohol intake.
- Sleep. Try to get 7 hours of sleep per night, or take naps when needed.
- Rest. Meditation, deep breathing and stretching can help you relax and reduce stress.
- Write it down. Keeping a journal with thoughts and feelings may help to let go of worries and fears.
View the Foundation’s Survivorship Series fact sheet on the Foundation’s website at lymphoma.org/publication for more info.
Care Partners
There are many ways you can help a loved one with lymphoma, as follows:
- Be present. The most important thing that a care partner can do is to “just show up.”
- Be prepared. Talk with the healthcare team so that you know what to expect throughout the treatment, how to manage symptoms and when to ask for help.
- Listen. Each person asks for help in different ways, verbally (through words) and nonverbally, and some may require more comfort while others are more action oriented.
- Avoid “cheerleading”. Do not disregard your love one’s negative feelings (sadness, anger or worry).
- Organize the help. A rush of sudden help upon diagnosis can make the situation harder to manage and create unproductive tension.
- Set up remote access with computer and/or phone access. This is helpful for regular communication with your loved one.
- Offer rides. This is important for people with decreased mobility or limited resources.
- Take notes. If you go into the appointments, write down notes with the doctor’s plan, medications, potential side effects and other relevant information.
Patients and their care partner are encouraged to keep copies of all medical records. This includes test results as well as information on the types, amounts, and duration of all treatments received. Medical records are important for keeping track of any side effects resulting from treatment or potential disease recurrences. The Foundation can help patients manage this documentation.
View the Care Partners fact sheet for more info.
Questions to Ask Your Healthcare Team
- What is my exact diagnosis? What subtype of lymphoma do I have? May I have a copy of the report from the pathologist?
- What is the stage of my disease? In what area of the body is it specifically located?
- What are my treatment choices? Which do you recommend for me and why? Would choosing one treatment prevent me from getting a different kind of treatment later on? How are the different treatments administered?
- Do I need more than one type of treatment?
- What is the goal of treatment? What are the expected benefits of each type of treatment?
- How will we know if the treatment is working? What tests will I need to determine if treatment is working, and how often will I need to be tested?
- How long will the treatment last?
- What are the chances the treatment will be successful?
- What is a clinical trial? Are clinical trials available that are studying new treatments for my type of lymphoma? Would a clinical trial be appropriate for me? How would I benefit? Are there any drawbacks of participating in a clinical trial?
- Will I be able to work during treatment? Will I be able to drive or take public transportation during my treatment?
- Should I take care of other medical or dental issues before I start treatment?
- How much will the treatment cost? Will my insurance cover some or all of it? What will my out-of-pocket costs be?

The Foundation’s Programs and Services

Lymphoma Care Plan
Keeping your information in one location can help you feel more organized and in control. This also makes it easier to find information pertaining to your care and saves valuable time. The Foundation’s Lymphoma Care Plan document organizes information on your health care team, treatment regimen, and follow-up care. You can also keep track of health screenings and any symptoms you experience to discuss with your health care provider during future appointments. The Lymphoma Care Plan document can be accessed by visiting lymphoma.org/publications.

Patient Education Programs
The Foundation also offers a variety of educational activities, including live meetings and webinars for individuals looking to learn directly from lymphoma experts. These programs provide the lymphoma community with important information about the diagnosis and treatment of lymphoma, as well as information about clinical trials, research advances and how to manage/cope with the disease. These programs are designed to meet the needs of a lymphoma patient from the point of diagnosis through long-term survivorship. To view our schedule of upcoming programs, please visit lymphoma.org/programs.

Lymphoma Resource Center
The Helpline staff are available to answer your general questions about lymphoma and treatment information, as well as provide individual support and referrals to you and your loved ones. Callers may request the services of a language interpreter. The Foundation also offers a one-to-one peer support program called the Lymphoma Support Network and clinical trials information through our Clinical Trials Information Service. For more information about any of these resources, visit our website at lymphoma.org, or contact the Foundation’s Lymphoma Resource Center at (800) 500-9976 or [email protected].
Para información en español, por favor visite lymphoma.org/es(for information in Spanish please visit lymphoma.org/es).

Lymphoma Support Network
The Foundation’s one-to-one peer support program – Lymphoma Support Network – connects patients and care partners with volunteers who have experience with lymphomas, similar treatments, or challenges, for mutual emotional support and encouragement. You may find this useful whether you or a loved one is newly diagnosed, in treatment, or in remission. For more information about this program, please contact the Foundation’s Lymphoma Resource Center at (800) 500-9976 or visit lymphoma.org/resources/supportservices/lsn.

Clinical Trials Information Service
The Foundation provides a “Clinical Trials Information Service” to increase awareness about trials being conducted at cancer treatment centers nationwide. Upon request, our Helpline staff can conduct a customized search for potential lymphoma treatment trials in a patient’s area. Trial search results can be mailed or emailed so that they may be discussed with the patient’s treating healthcare team and loved ones. Individuals interested in having a trial search conducted for them can contact the Lymphoma Resource Center at (800) 500-9976 or [email protected] or complete a trial search request form on our website at lymphoma.org/ctis.
© 2025 Lymphoma Research Foundation
Disclaimer: The Lymphoma Research Foundation is a national nonprofit organization based in the United States (U.S.) with educational programs and resources which are intended for a U.S. based audience. These programs and resources are intended for educational purposes only and are not a substitute for medical advice. Individuals who use Foundation programs and services are advised to consult a medical professional for medical advice, diagnoses, or treatment. Foundation programs and resources address available lymphoma/CLL treatments in the United States and information on drug approvals by the U.S. Food and Drug Administration (FDA).
The Foundation does not endorse any treatments, products, or services mentioned in its resources. The information provided is for informational purposes only and should not be considered as an endorsement. The Foundation shall not be liable for any direct, indirect, incidental, special, consequential, or punitive damages arising out of the use of its programs and resources, to the extent permitted by law. You assume full responsibility for any actions taken based on the information provided.
For individuals outside of the U.S. seeking information, the Foundation recommends the Lymphoma Coalition. The Lymphoma Coalition is a global network of worldwide nonprofit/NGO lymphoma patient organizations with information appropriate for non-U.S.-based audiences. Additional information can be found by visiting their website at https://lymphomacoalition.org/.
All content provided by the Foundation is protected by intellectual property laws. You may not reproduce, distribute, or otherwise use the content without the Foundation’s prior written consent.
The Lymphoma Research Foundation appreciates the expertise and review of our Editorial Committee:
Co-Chair: Leo I. Gordon, MD, FACP
Robert H. Lurie Comprehensive Cancer Center of Northwestern University
Co-Chair: Kristie A. Blum, MD
Emory University School of Medicine
Jennifer E. Amengual, MD
Columbia University
Carla Casulo, MD
James P. Wilmot Cancer Institute
Shana Jacobs, MD
Children’s National Hospital
Patrick Conner Johnson, MD
Massachusetts General Hospital
Manali Kamdar, MD
University of Colorado
Ryan Lynch, MD
University of Washington
Peter Martin, MD
Weill Cornell Medicine
Lia Palomba, MD
Memorial Sloan Kettering Cancer Center
Tycel Phillips, MD
City of Hope
Pierluigi Porcu, MD
Thomas Jefferson University
Neha Mehta-Shah, MD, MSCI
Washington University School of Medicine St. Louis
Sarah Rutherford, MD
Weill Cornell Medicine
Supported through grants from:


