
Diagnostic and Biomarker Testing
Understanding Lymphoma and Chronic Lymphocytic Leukemia (CLL)
Introduction
Doctors use different diagnostic tests (clinical tests used to identify a disease) to determine if a patient has lymphoma or CLL, but a biopsy is the only way to confirm a lymphoma diagnosis.
How are Lymphomas and CLL Diagnosed?
Some patients with lymphoma and chronic lymphocytic leukemia (CLL) do not have any obvious signs or symptoms of the disease at the time of diagnosis. Their doctors might detect the disease during routine blood tests and/or a physical examination. For others, it is discovered when symptoms such as fevers, unusual sweating or unintentional weight loss occur and patients go to the doctor because they are worried, uncomfortable, or not feeling well.
Diagnostic Tests Used in Lymphoma
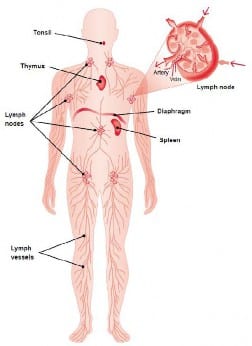
Doctors use different diagnostic tests (clinical tests used to identify a disease) to determine if a patient has lymphoma or CLL, but a biopsy is the only way to confirm a lymphoma diagnosis. In this procedure, a piece of the abnormal tissue is removed from the body and examined under a microscope. The affected tissues in lymphoma are usually lymphnodes (bean-shaped structures that help the body fight infection, Figure1). There are 3 main types of biopsies (Table1).
Biopsies are examined by a pathologist(doctor who specializes in the diagnosis of diseases by studying the cells from a patient’s body fluids and tissue samples). A hemato-pathologist (pathologist who has undergone additional training in the diagnosis of blood diseases, including lymphoma) typically examines these samples. These specialists identify and classify the lymphoma cells by looking at their shape and size under a microscope.
An oncologist (doctor who specializes in treating patients with cancer) or hematologist (doctor who specializes in treating patients with blood cancers and other blood disorders) uses the pathologist’s report, along with results of other diagnostic tests, to confirm a diagnosis. Diagnosing the type of lymphoma can sometimes be difficult and may require multiple medical experts.
Table 1: The Three Main Types of Biopsies
| Type of Biopsy | Description |
|---|---|
| Excisional or Incisional Biopsy | – A surgeon cuts through the skin to remove an entire lymph node (excisional biopsy) or a large portion of a lymph node or other tissue (incisional biopsy). – If the lymph node is close to the skin surface, the procedure can be done under local anesthesia (a local injection that numbs only the affected area). – If the lymph node is in the chest or abdomen, the patient is sedated (the patient relaxes to the point of sleep but can wake up if needed to communicate) and the surgeon removes the tissue. – Best to establish an initial diagnosis of lymphoma because it allows the removal of bigger samples than other biopsy procedures. |
| Core Needle Biopsy | – A large needle is inserted into the lymph node and a small tissue sample is removed using a syringe attached to the needle. This can be done under local anesthesia, and stitches are usually not required. – Used when the affected lymph nodes are difficult to reach with excisional biopsy, or when there are medical reasons for avoiding an excisional or incisional biopsy. |
| Fine Needle Aspirate Biopsy | – This procedure is performed with a very thin needle that is smaller than the kind used for a core needle biopsy. – May be used if a core needle biopsy is not possible. However, this test does not provide enough information to establish a diagnosis of lymphoma in many cases. |
If the biopsy sample is small it may not be an accurate example of the rest of the lymph node. In these instances, a repeat biopsy may be needed to establish a diagnosis. It takes an experienced hematopathologist working with the hematologist or oncologist to determine the need for more tissue sampling. The results for this exam are usually available in 5 to 10 business days, but it may take longer for Hodgkin and T-cell non-Hodgkin lymphomas (may take from 10 days to 1 month). This timeline can be longer if additional testing is needed to identify the exact type of lymphoma you have or if the team decides to seek a second opinion.
The following tests may also be used to help with the diagnosis:
- Bone marrow biopsy: A bone marrow biopsy involves removing a small amount of bone marrow (the spongy tissue inside the bones) and examining it for the presence of lymphoma cells. A bone marrow aspiration is similar to a bone marrow biopsy, except it involves removing only the liquid portion of the marrow using a fine needle. A bone marrow biopsy and aspiration are not typically used for initial diagnosis, but might be used to evaluate the stage (extent) of the lymphoma and also to collect additional tumor tissue for specialized testing.
- Immunophenotyping: Routinely performed in the diagnosis of most lymphomas, this is a test that studies the molecules (antigens) present on cells collected from the biopsy. Antigens are specific to different cell types, just as landmarks are specific to different cities. Using this test, a hemato-pathologist can tell apart lymphoma cells from healthy cells and look for antigens that are relevant for treatment (some treatments may only work if cancer cells have a specific antigen).
- Genetic testing: tests that look for abnormalities in the genes (small pieces of deoxyribonucelic acid [DNA], the molecule that carries genetic information inside the cells and determines a person’s traits) and/or chromosomes (threadlike structures that contain the genes) of the cells collected from the biopsy.
- Complete blood count (CBC) with differential: a test that determines the amount of each type of white blood cell relative to the total number of cells. Some lymphomas are characterized by circulating lymphoma cells and a blood test with immunophenotyping may be sufficient for diagnosis (no need for a biopsy in these cases).
- Erythrocyte sedimentation rate (ESR): a test that measures how quickly erythrocytes (red blood cells) separate from the blood sample. Elevated ESR can be a signal of inflammation in the body
- Comprehensive metabolic panel: a blood test that measures the levels of different substances to check if the liver and kidneys are working properly. This is also important prior to chemotherapy with drugs that can affect the patient’s liver and kidneys.
- Imaging scans: computed tomography (CT, uses X-rays to produce images of the inside of the body) and/or positron emission tomography (PET, uses a special dye that is injected into the patient and shows where the cancer is located). If the patient has neurologic (brain and/or nerve) symptoms, magnetic resonance imaging (MRI, uses a powerful magnet to produce detailed images of the inside of the body) is used to look for signs of cancer in the brain.
- Testing for infection with the human immunodeficiency virus (HIV) and hepatitis B and C viruses. Some lymphoma treatments can reactivate (wake up) dormant virus in the patient, and doctors test for viral infections to prevent complications from treatment.
What is Biomarker Testing?
When making decisions about cancer diagnosis and treatment, doctors may look for biomarkers(also called tumormarkers). Biomarkers are molecules produced by cancer cells (like certain genes, proteins, or other substances) that can be measured in the laboratory. Biomarker testing uses different methods to look for changes in these biomarkers (like mutations [permanent modifications] in genes, or abnormal amounts of a protein) in samples taken from the patient (biopsies, blood samples, or other body fluids). If a biomarker test is paired with a specific treatment, it can be called a companion diagnostic test. This is a biomarker test that lets your health care team know if that specific treatment is right for you.
Biomarker testing helps doctors understand which type of lymphoma you have and how well you will do after treatment. It may provide valuable information about cancer in three specific cases:
- Is the cancer more likely to grow and spread? Some changes in cancer cells may cause them to grow faster and migrate to other sites of the body.
- Which treatments are more appropriate and which ones are not likely to work? Some treatments may only work if cancer cells have a specific biomarker. This information can spare patients from treatments that likely will not work.
- Is the treatment working? A reduction in cancer biomarkers indicates that there is less cancer in the body. On the other hand, an increase in cancer biomarkers may indicate that the cancer is progressing or has relapsed (returned after treatment).
Each person may have a specific set of biomarkers that are different from another person with the same type of cancer. Biomarker testing is a form of precisionor personalizedmedicinethat can help doctors make decisions based on the characteristics of your cancer and tailor medical care to your specific needs. This is different than standard cancer treatment, which is based on the type and size of the cancer, and whether it has spread. While not all cancer patients may benefit from biomarker testing, it is important that you discuss with your health care team if biomarker testing is right for you.
Types of Biomarker Testing
There are many different types of biomarker tests, but they mainly focus on finding mutations in genes or changes on a given protein. While some detect changes that can be inherited (passed from parent to child, called germline mutations), most biomarker tests look for changes that happen after birth (called somatic mutations) and cannot be passed on to your family.
The methods used for biomarker testing depend on the type of biomarker your doctor is looking for, as described in Table 2. Most tests used to guide cancer treatment look for genetic markers, but some look for proteins or other kinds of markers.
Table 2: Examples of Biomarker Testing in Cancer
| Type of Biomarker | Examples of Biomarker Testing |
|---|---|
| Genetic biomarkers | Tests that look for changes in your DNA: – Genetic sequencing: determines the order of the four building blocks (called bases) that form the DNA. The order of DNA bases (genetic sequence) in your genes determines which proteins the body makes and what they do. The information in that specific gene may be relevant to your cancer. – Genomic sequencing: determines the sequence of all the genes present in the organism (also called genome). The genome has all the information the body needs to develop and function. This provides a complete picture of all your genetic material and helps doctors identify your cancer subtype (also called genomic profiling). – Next-generation sequencing: fast sequencing of many genes at the same time and helps doctors identify thousands or even hundreds of thousands of variants (genetic changes) in a single test. Tests that look for DNA from cancer cells: – Circulating tumor DNA (ctDNA): a test to detect DNA released from cancer cells into the bloodstream. It is the most widely used blood biomarker in cancer. Monitoring ctDNA in the blood may help doctors detect and treat cancer. |
| Protein biomarkers | Tests that look for the presence of specific proteins: – Immunophenotyping: studies the antigens (proteins) present on the cancer cells collected from the biopsy (see above). This test can be done using flow cytometry (cancer cells that have the antigens on their surface become fluorescent) or immunohistochemistry (cancer cells that have the antigens on their surface show color). |
| Others | Minimal residual disease (MRD): a sensitivity test to detect a small number of cancer cells in a sample of blood or bone marrow after treatment. An MRD-negative status means that no cancer cells were detected. The sensitivity of MRD tests can be higher, depending on the method used. Lower levels of MRD (fewer cancer cells remaining after the completion of treatment) and MRD-negative tests (no cancer cells detected) may indicate a patient will have a longer remission (no signs or symptoms of cancer). |
How is biomarker testing useful in lymphoma and chronic lymphocytic leukemia treatment?
Biomarkers may broadly be classified into two classes –diagnostic biomarkers and prognostic biomarkers. Biomarkers can be used to diagnose some lymphoma subtypes, evaluate if a patient is likely to respond to a specific treatment, and determine a patient’s prognosis (how well a patient will do). Some examples are described below.
Diffuse Large B-Cell Lymphoma
Doctors use genomic profiling to identify the subtype of diffuse large B-cell lymphoma (DLBCL), the most common form of non-Hodgkin lymphoma (NHL). This test determines the cell that originated the cancer and divides DLBCL in two subtypes, germinal center B-cell-like (GCB) and activated B-cell-like (ABC). This is important because patients with the GCB subtype may have a better response to chemotherapy than those with the ABC subtype. Doctors also check for two proteins called MYC and BCL2, which helps to tell apart DLBCL from a more aggressive(fast-growing) type called high-grade B-cell lymphoma. This type of lymphoma is treatable, but more likely to relapse than DLBCL.
Anaplastic Large Cell Lymphoma
Testing for an abnormal form of a protein called anaplastic lymphoma kinase (ALK) in patients with anaplastic large cell lymphoma (ALCL). ALK inhibitors can be used in patients with relapsed ALK-positive ALCL. Another important biomarker for ALCL is a protein called CD30. Patients who have ALCL that is positive for CD30 can receive brentuximab vedotin (Adcetris), an antibody-drug conjugate (a antibody targeting CD30 attached to a chemotherapy drug) as frontline (initial) treatment regardless of ALK status.
Chronic Lymphocytic Leukemia
In chronic lymphocytic leukemia (CLL), biomarker testing for CD5, CD19, CD23 and dimCD20 (proteins located at the surface of cancer cells) help doctors tell apart CLL from other types of leukemia. Patients with CLL who have mutations in the immunoglobulin heavy chain variable (IGHV) gene have longer responses to combined treatment with chemotherapy and immunotherapy (drugs that use the body’s immune response to fight cancer, see Immunotherapy and Other Targeted Therapieson LRF’s website lymphoma.org/publications). Another important biomarker in some patients with CLL is a mutation in chromosome 17 called a deletionor del(17p). This means that part of the chromosome 17 is missing in these patients, which influences treatment. Patients with CLL who have this biomarker may not respond to immunotherapy with rituximab (Rituxan).
Other Types of Lymphoma
Some cancer treatments may only work in patients who have certain biomarkers. An example are immune checkpoint inhibitors, which are used to treat classical Hodgkin lymphoma (cHL) and primary mediastinal B-cell lymphoma (PMBCL). These drugs work better in patients who have high levels of a protein called programmed cell death ligand 1 (PD-L1), have a deficient mismatch repair (dMMR, a system that repairs damages in the DNA) and a high tumor mutational burden (TMB, number of mutations found in cancer cells).
It is important to highlight that having a specific biomarker does not mean that you will respond to a given treatment. For example, your body may breakdown the drug in a way that makes it less effective. The results from biomarker testing may also change over time because cancer cells grow fast and may change as they multiply
How can patients access biomarker testing?
Biomarker testing is not available in every hospital. Your samples are sent to a special laboratory where they will be tested. If your health care team decides that biomarker testing is right for you, talk with your doctors about how you can access these tests. The cost will depend on the type of test, the type of cancer, and the insurance plan. It is important that you check your insurance plan to see if and when it covers biomarker testing. Private insurance often covers the costs of biomarker testing when there is enough proof that it is needed to establish a treatment plan. Medicaid and Medicare also cover some biomarker tests in people who have advanced cancer.
You may also access biomarker testing by joining a clinical trial, which can also cover costs. Talk to your health care team to see if joining a clinical trial is the right approach for you. For more information about relevant legislation and initiatives in your area, see the Cancer Network Action website (visit fightcancer.org/what-we-do/access-biomarker-testing).
Latest Advances in Testing
There are many different types of lymphoma, which differ in the way they develop and spread, as well as in the way they are treated. Because of this, researchers need to study a large number of patients to see if a given substance (a protein or gene, for example) is a biomarker for a certain type of lymphoma. Many biomarkers are still not well understood or do not have a corresponding therapy. While standard clinical trials were traditionally based on the type of cancer, new clinical trials in cancer are using biomarkers to select patients who can participate. Research is also ongoing to discover new biomarkers for diagnosis (used to identify a disease), treatment selection (used to identify individuals who are more likely to respond to treatment or have a specific side effect), prognostic (how well a patient will do), risk (used to identify the chances of having lymphoma), and monitoring (used to evaluate how the disease evolves over time) of lymphoma.
Some of these clinical trials are described below:
- Genetic sequencing for relapsed or refractory mantle cell lymphoma and advanced lymphoma.
- Genomic sequencing for lymphoma.
- ctDNA testing for NHL.
- MRD testing for B-cell NHL such as Burkitt Lymphoma, DLBCL, primary central nervous system lymphoma, and primary mediastinal lymphoma.
For more information about ongoing biomarker clinical trials in lymphoma, please visit the Clinical Trials Information Service on the Foundation’s website (visit lymphoma.org/resources/ supportservices/ctis/) or talk to your health care team.
Lymphoma Care Plan
Keeping your information in one location can help you feel more organized and in control. This also makes it easier to find information pertaining to your care and saves valuable time. The Foundation’s Lymphoma Care Plan document organizes information on your health care team, treatment regimen, and follow-up care. You can also keep track of health screenings and any symptoms you experience to discuss with your health care provider during future appointments. The Lymphoma Care Plan document can be accessed by visiting lymphoma.org/publications.
Patient Education Programs
The Foundation also offers a variety of educational activities, including live meetings and webinars for individuals looking to learn directly from lymphoma experts. These programs provide the lymphoma community with important information about the diagnosis and treatment of lymphoma, as well as information about clinical trials, research advances and how to manage/cope with the disease. These programs are designed to meet the needs of a lymphoma patient from the point of diagnosis through long-term survivorship. To view our schedule of upcoming programs, please visit lymphoma.org/programs.
Lymphoma Resource Center
The Foundation’s Lymphoma Resource Center staff are available to answer your general questions about lymphoma and treatment information, as well as provide individual support and referrals to you and your loved ones. Callers may request the services of a language interpreter. The Foundation also offers a one-to-one peer support program called the Lymphoma Support Network and clinical trials information through our Clinical Trials Information Service. For more information about any of these resources, visit our website at lymphoma.org, or contact the Lymphoma Resource Center at (800) 500-9976 or [email protected].
Para información en Español, por favor visite lymphoma.org/es. (For Information in Spanish please visit lymphoma.org/es).
© 2026 Lymphoma Research Foundation
Disclaimer: The Lymphoma Research Foundation is a national nonprofit organization based in the United States (U.S.) with educational programs and resources which are intended for a U.S. based audience. These programs and resources are intended for educational purposes only and are not a substitute for medical advice. Individuals who use Foundation programs and services are advised to consult a medical professional for medical advice, diagnoses, or treatment. Foundation programs and resources address available lymphoma/CLL treatments in the United States and information on drug approvals by the U.S. Food and Drug Administration (FDA).
The Foundation does not endorse any treatments, products, or services mentioned in its resources. The information provided is for informational purposes only and should not be considered as an endorsement. The Foundation shall not be liable for any direct, indirect, incidental, special, consequential, or punitive damages arising out of the use of its programs and resources, to the extent permitted by law. You assume full responsibility for any actions taken based on the information provided.
For individuals outside of the U.S. seeking information, the Foundation recommends the Lymphoma Coalition. The Lymphoma Coalition is a global network of worldwide nonprofit/NGO lymphoma patient organizations with information appropriate for non-U.S.-based audiences. Additional information can be found by visiting their website at https://lymphomacoalition.org/.
All content provided by the Foundation is protected by intellectual property laws. You may not reproduce, distribute, or otherwise use the content without the Foundation’s prior written consent.
The Lymphoma Research Foundation appreciates the expertise and review of our Editorial Committee:
Co-Chair: Leo I. Gordon, MD, FACP
Robert H. Lurie Comprehensive Cancer Center of Northwestern University
Co-Chair: Kristie A. Blum, MD
Emory University School of Medicine
Jennifer E. Amengual, MD
Columbia University
Carla Casulo, MD
James P. Wilmot Cancer Institute
Shana Jacobs, MD
Children’s National Hospital
Patrick Conner Johnson, MD
Massachusetts General Hospital
Manali Kamdar, MD
University of Colorado
Ryan Lynch, MD
University of Washington
Peter Martin, MD
Weill Cornell Medicine
Lia Palomba, MD
Memorial Sloan Kettering Cancer Center
Tycel Phillips, MD
City of Hope
Pierluigi Porcu, MD
Thomas Jefferson University
Neha Mehta-Shah, MD, MSCI
Washington University School of Medicine St. Louis
Sarah Rutherford, MD
Weill Cornell Medicine
Supported through grants from:


